

Understanding Myopia Progression in Children
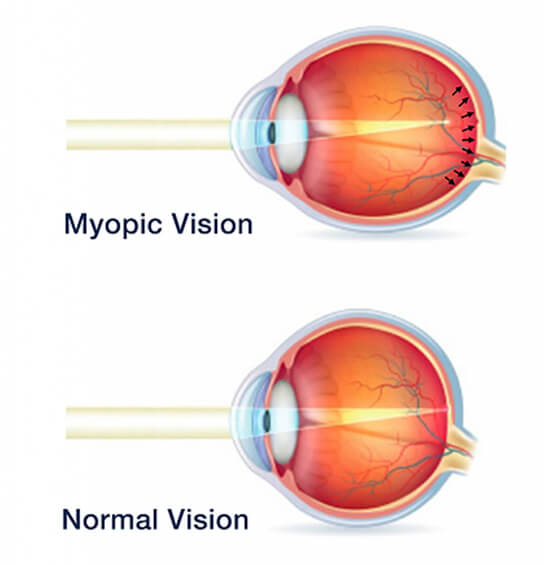
Myopia, also known as short-sightedness, causes distant objects to appear blurred while nearer objects are usually clearer. In many children with myopia, this happens because the eye has grown longer from front to back, causing light to focus in front of the retina rather than directly on it.
Glasses or contact lenses can correct the blurred vision, but seeing clearly does not necessarily mean that the myopia has stopped progressing. During childhood, the prescription and the length of the eye can continue to change as the child grows.
For parents, an important question is therefore not only “Does my child have myopia?”, but also “Is the myopia progressing, and how quickly is it changing?”
Why does childhood myopia progress?
Myopia progression is influenced by several factors rather than a single cause. One of the most important considerations is the age at which myopia begins. Children who develop myopia at a younger age generally have more years during which their myopia may continue to progress.
Other factors may also contribute to a child’s overall risk and progression pattern, including:
- the child’s age and age when myopia first developed;
- how quickly the prescription has changed over previous eye examinations;
- family history of myopia;
- visual habits and the amount of time spent on near work;
- time spent outdoors; and
- the child’s individual eye growth and clinical findings.
These factors need to be considered together. For example, having myopic parents does not automatically mean that a child’s myopia will progress rapidly, and screen use alone does not explain why an individual child becomes myopic.
Parents who would like to understand the role of visual habits can read our guide on screen time, outdoor time and childhood myopia .
What does myopia progression mean?
Myopia progression generally refers to myopia becoming stronger over time. This may be seen as an increasingly negative spectacle prescription, continued growth in the axial length of the eye, or both.
This is why a single prescription provides only part of the picture. Looking at changes over time can give a more useful understanding of how a child’s myopia is developing.
Progression also varies between children. Two children with the same spectacle prescription today may not necessarily follow the same pattern over the next few years. Age, previous progression and other clinical findings all help provide context.
What should parents pay attention to?
Children do not always notice that their myopia is progressing, particularly when their current glasses or contact lenses still provide clear vision. Regular eye examinations are therefore more useful than relying on symptoms alone.
Closer monitoring may be particularly relevant when:
- myopia develops at a relatively young age;
- the spectacle prescription has repeatedly increased between eye examinations;
- there is a strong family history of myopia;
- previous examinations have already shown continued progression; or
- a child is already using a myopia-control treatment and parents want to understand how the eyes are changing over time.
If you are unsure whether the changes in your child’s prescription require closer attention, our guide on when parents should worry about myopia progression explains the main signs and measurements in more detail.
Why progression matters
Myopia is common among children in Singapore, but the degree and rate of progression are not the same for every child. In general, developing myopia at a younger age is associated with a greater likelihood of reaching higher levels of myopia later in life.
This does not mean that every child with myopia will develop high myopia. It does mean that identifying progression early and monitoring how the eyes change over time can help parents and their optometrist make more informed decisions about whether active myopia control should be considered.
The next question is therefore not simply whether a child needs clearer glasses, but whether their myopia is progressing and whether additional steps may be appropriate to help slow that progression.
CONSEQUENCES OF HIGH MYOPIA
While high myopia can be managed through several common treatment options, it still poses high health risks that can severely impact quality of life over time.

Glasses become thicker and heavier with higher levels of myopia. High-index spectacle lenses to reduce thickness also add extra expense to each pair of new glasses.
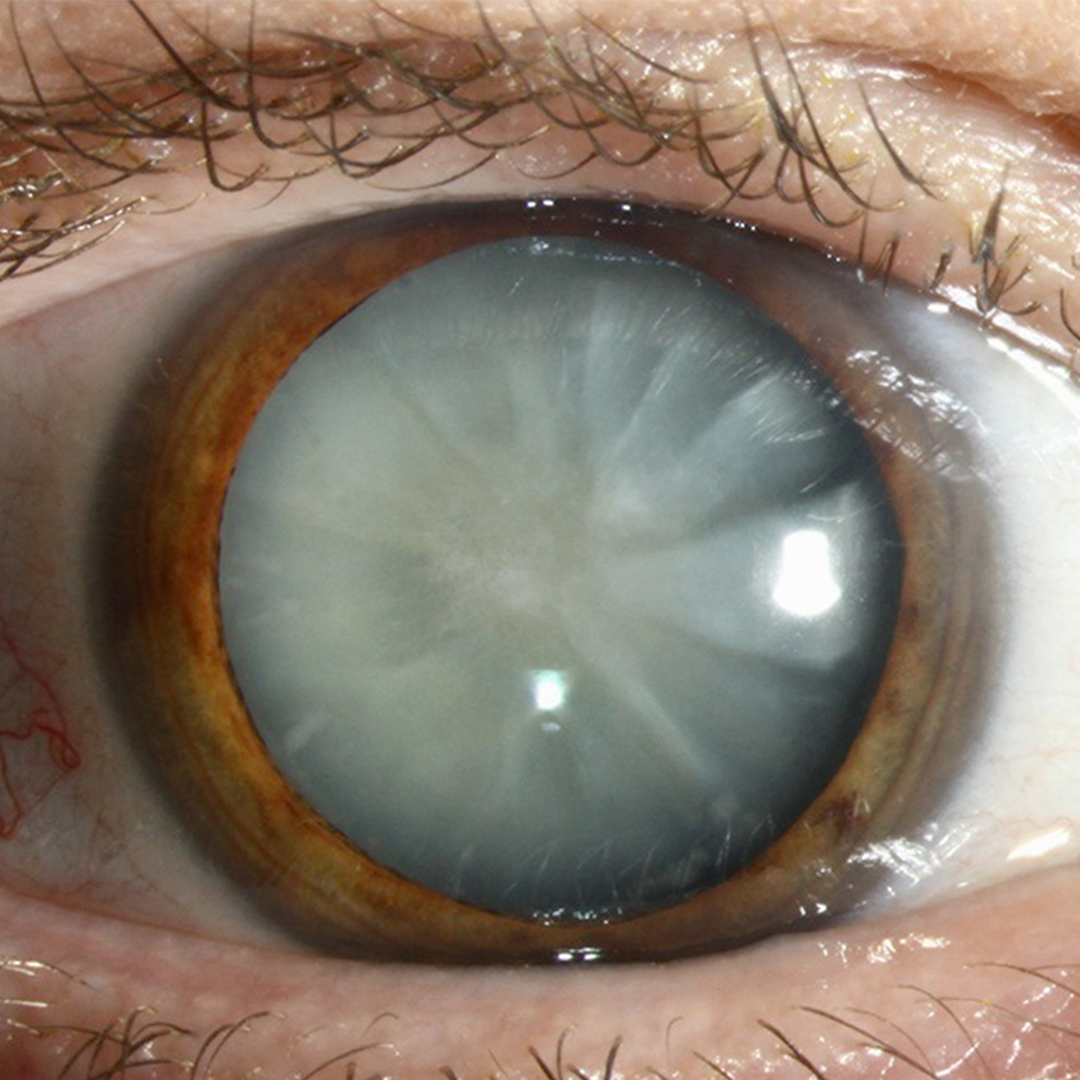
High myopia is associated with cataract formation, and also increases the risk of complications during and after cataract surgery.

High myopia has been linked to a higher incidence of glaucoma, and development of more severe cases of glaucoma.
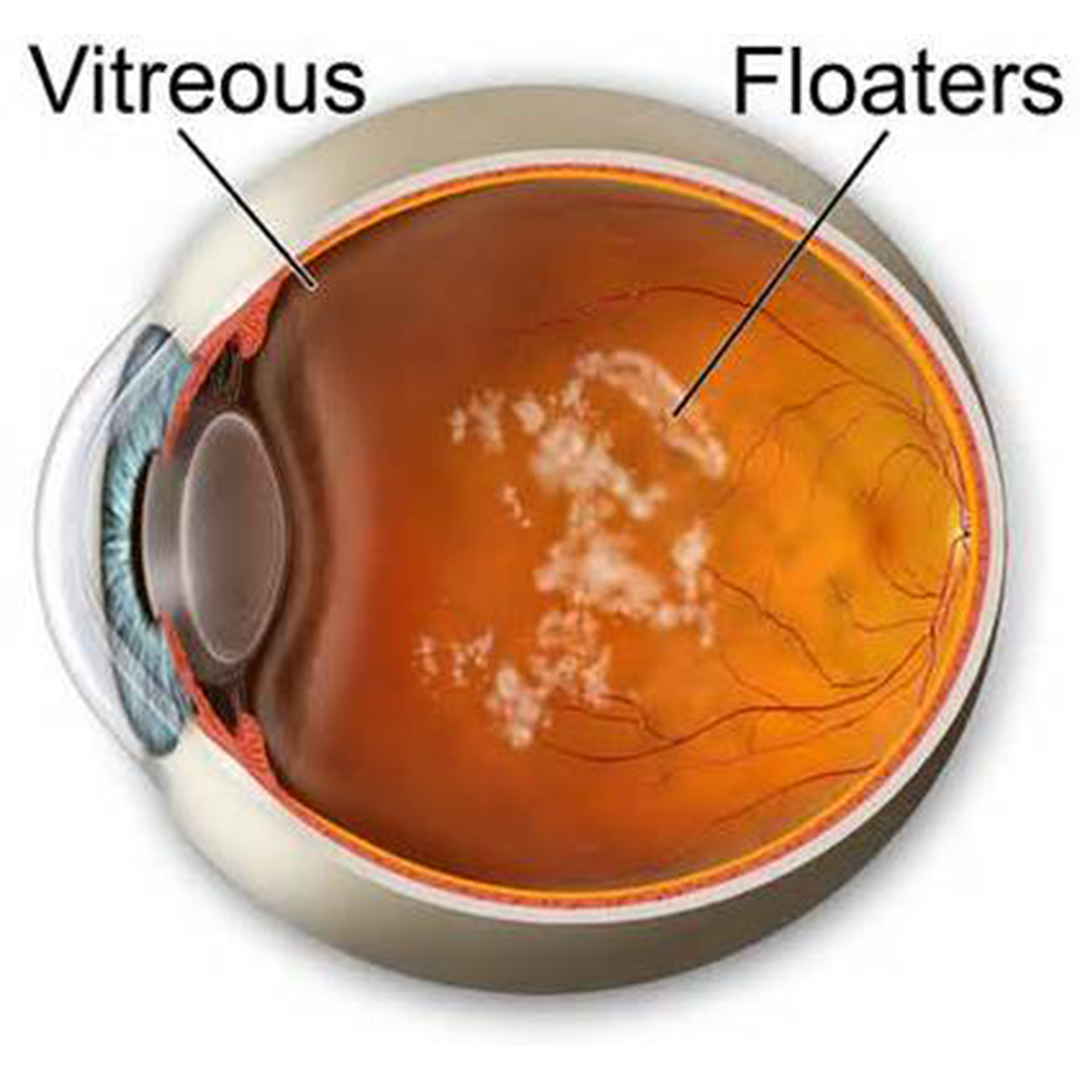
Myopia commonly causes earlier vitreous detachment, leading to many visually-disruptive spots and floaters and increases glare.
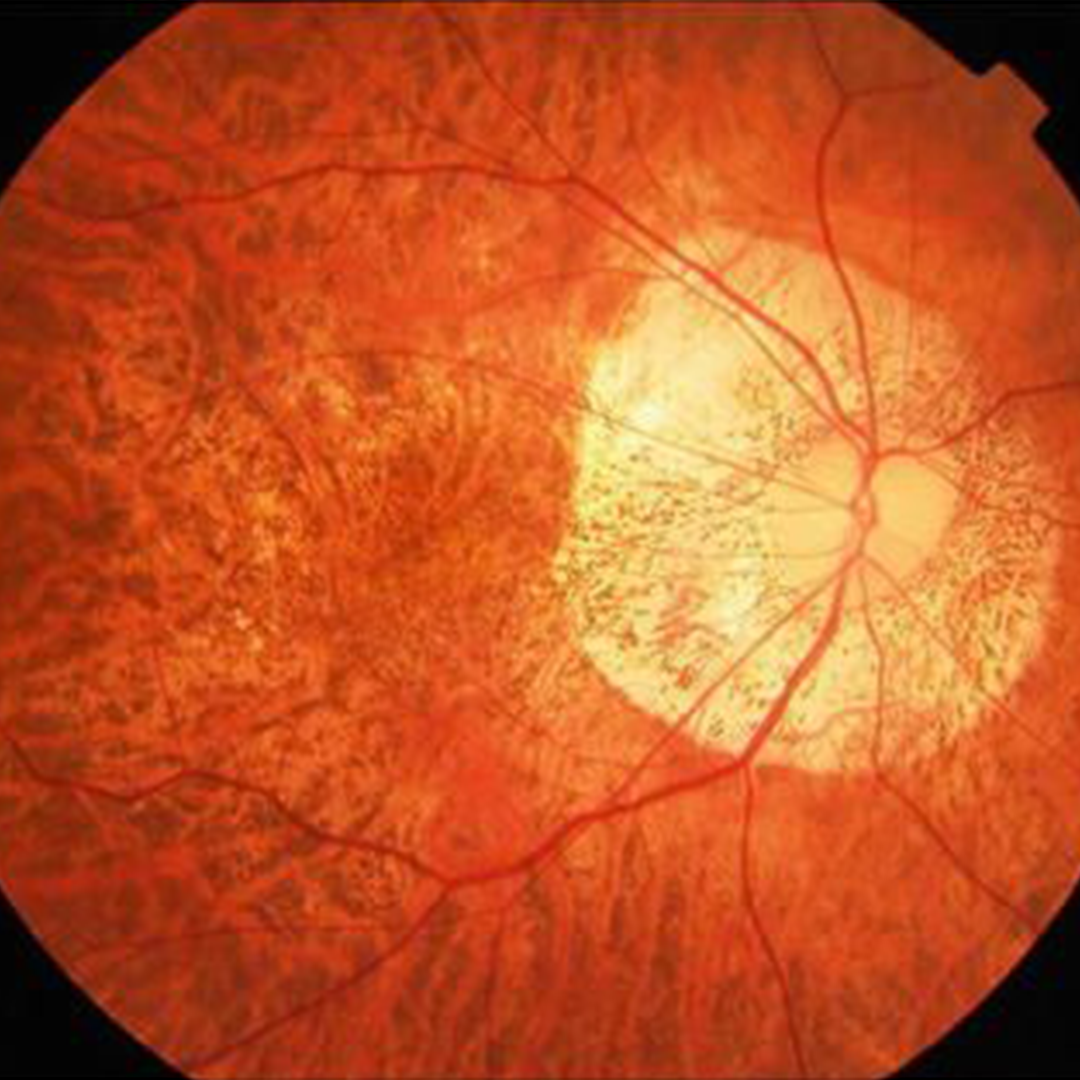
Thinning of the retina in a highly myopic eye increases the risk of developing myopic macular degeneration, causing loss of central vision.
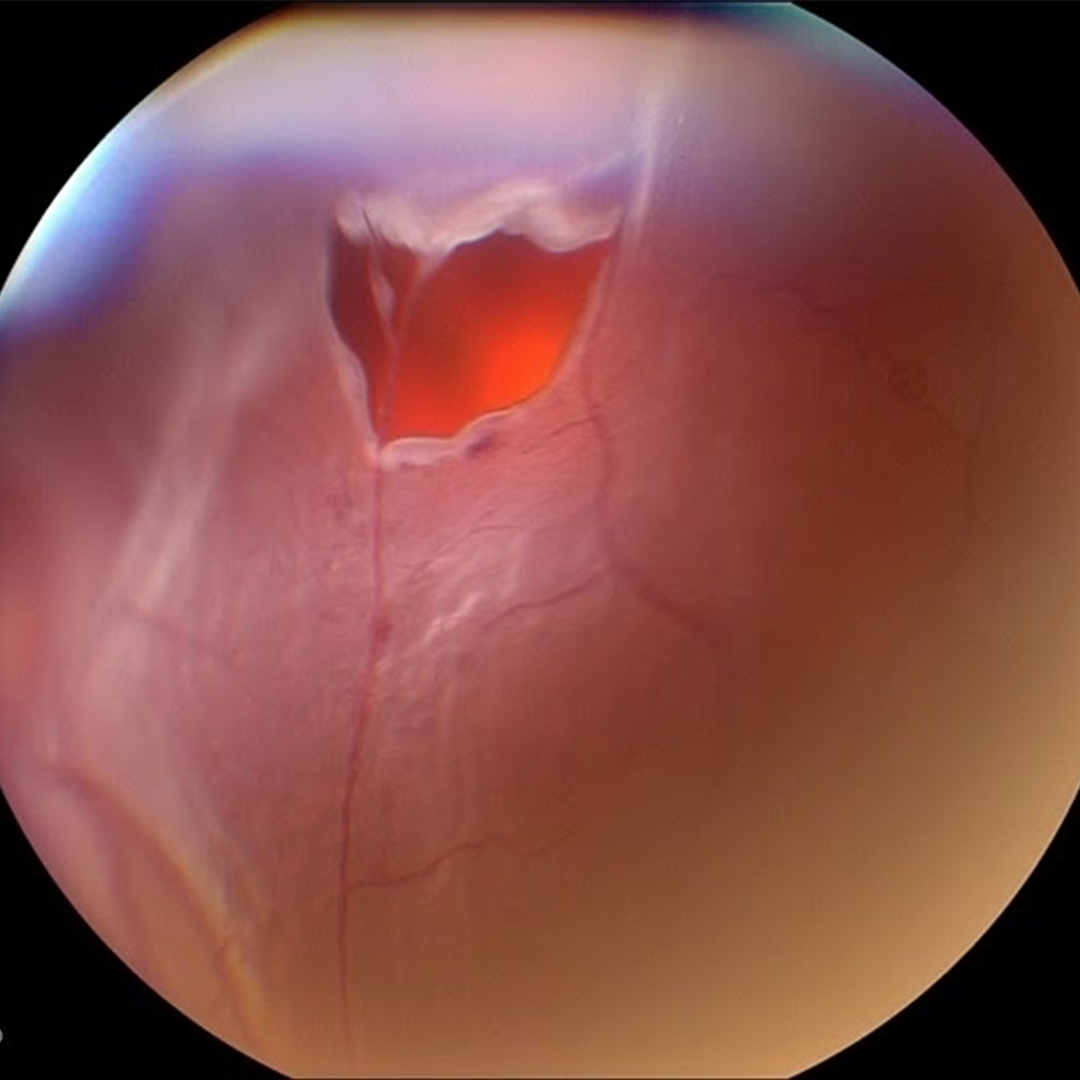
A small tear in the retina can quickly develop into a retinal detachment, which, if not detected and managed promptly, can lead to permanent vision loss.
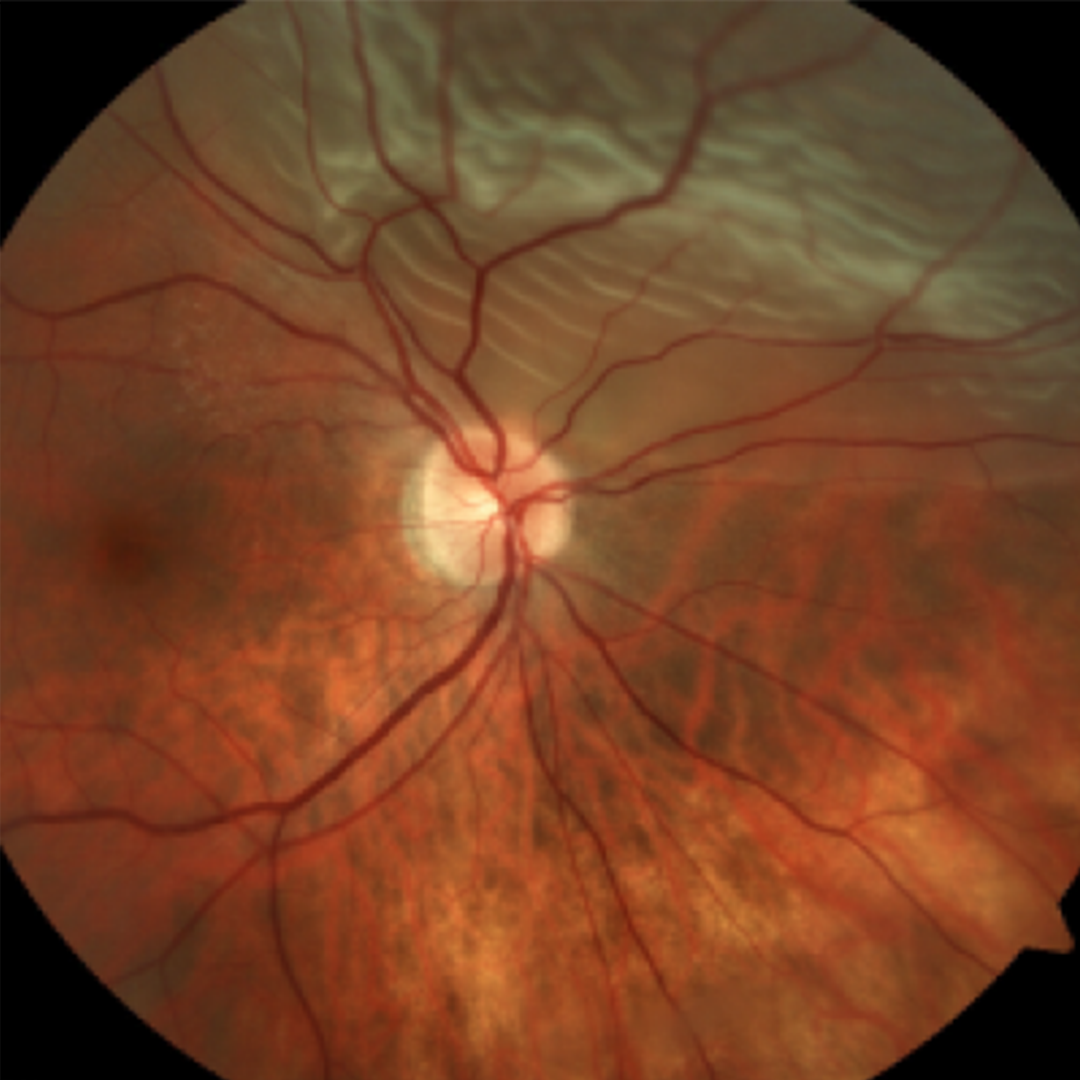
Symptoms of a retinal detachment may include flashes of light, sudden increase of floaters, and a large shadow moving across the line of sight.
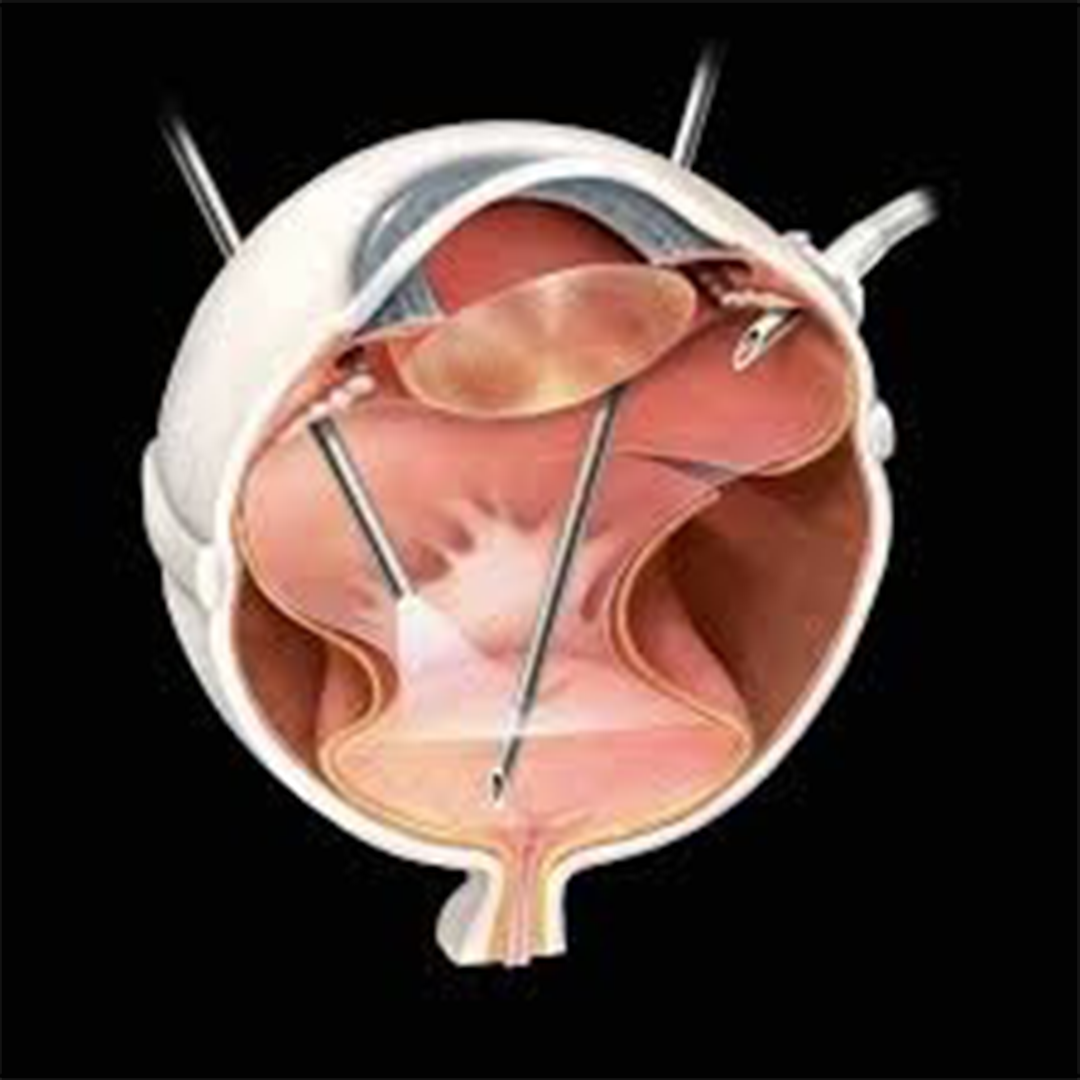
Retinal detachment surgery to repair a torn retina and restore sight is a complex, risky and invasive procedure. Vision may never fully return to normal.
When to Consider Myopia Control

If your child has myopia, getting the correct glasses or contact lenses is important for clear vision. However, correcting blurred vision and controlling myopia progression are not the same thing.
Myopia correction helps a child see clearly. Myopia control refers to strategies specifically intended to help slow the progression of myopia over time.
Not every child with myopia will progress at the same rate, and there is no single prescription level or age that automatically determines whether myopia-control treatment should begin. The decision is better made by looking at how the child’s eyes are changing over time, together with their age, prescription, eye health, family history and other clinical findings.
Why does the age of onset matter?
Children who develop myopia at a younger age generally have more years during childhood in which their myopia may continue to progress. This can increase the likelihood of reaching higher levels of myopia later.
For this reason, a younger child who has recently developed myopia may benefit from closer monitoring even if the current prescription is still relatively low.
Age is only one part of the assessment. The rate of prescription change, eye growth and the child’s overall clinical picture also need to be considered before deciding whether active myopia control is appropriate.
Signs that closer myopia monitoring may be useful
A myopia assessment may be worth considering when:
- your child developed myopia at a relatively young age;
- their spectacle prescription has increased repeatedly between eye examinations;
- previous measurements show continued growth in the length of the eye;
- there is a strong family history of myopia;
- your child’s myopia is progressing despite already using a myopia-control treatment; or
- you would like to understand whether the current rate of change warrants active myopia management.
A single prescription change does not always tell the whole story. Progression is best interpreted over time and alongside other measurements rather than using one universal cut-off for every child.
Why consider slowing myopia progression?
The purpose of myopia control is not to “cure” myopia or guarantee that it will stop progressing. The aim is to reduce the rate of progression where possible while maintaining clear, comfortable vision.
This matters because higher levels of myopia are associated with a greater lifetime risk of certain eye-health problems. Slowing progression during childhood may therefore help reduce the degree of myopia a child eventually develops.
The response to myopia-control treatment varies between children, which is why ongoing assessment and monitoring remain important even after a management option has been started.
Does every child with myopia need myopia-control treatment?
Not necessarily.
Some children may show relatively little change over time, while others may progress more quickly. The appropriate next step depends on the child’s individual risk factors, eye measurements, previous progression and practical considerations.
For some children, continued monitoring may be appropriate. For others, active myopia-control options may be worth discussing.
This is also why EMME does not treat one particular lens or treatment as the automatic choice for every child. Different options have different advantages, limitations and suitability considerations.
What if my child already wears glasses?
Ordinary single-vision glasses can provide clear distance vision, but they are not specifically designed to slow myopia progression.
For children who may benefit from active myopia control, options can include specialised myopia-control spectacle lenses, certain contact-lens approaches such as Ortho-K or daily disposable myopia-control lenses, and in some cases pharmacological treatment prescribed and monitored by an ophthalmologist.
The most appropriate option depends on the individual child rather than simply choosing whichever treatment appears to have the highest headline effectiveness figure.
When is the right time to have a myopia assessment?
Parents do not need to wait until a child reaches a very high prescription before asking about myopia progression.
If your child has recently developed myopia, has had repeated prescription changes, or you are concerned about how quickly their eyesight is changing, a myopia assessment can help establish a clearer baseline and determine whether closer monitoring or active myopia control should be considered.
The next step is to understand how your child’s myopia is progressing. In the next section, we explain how EMME assesses prescription changes, eye growth and other factors before discussing suitable management options.
Myopia Assessment at EMME Visioncare
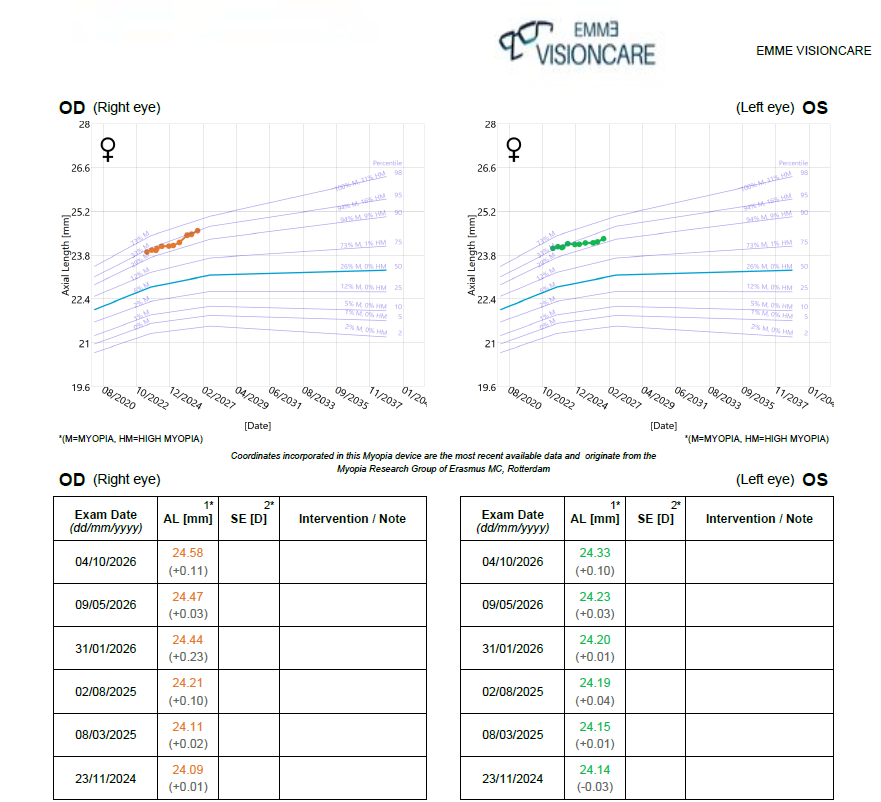
Choosing a myopia-control option should not be based on spectacle prescription alone. At EMME Visioncare, we assess how your child’s myopia has been changing over time and consider several clinical factors before discussing whether active myopia control may be appropriate.
This helps us answer three important questions:
- Is your child’s myopia progressing?
- How should the current measurements be interpreted in the context of their age and history?
- Which management options may be suitable for your child?
Reviewing your child’s myopia history
Understanding progression begins with looking at the pattern over time. Where previous records are available, we review changes in your child’s spectacle or contact-lens prescription together with their age, when myopia was first detected and any previous myopia-management treatment.
We also consider relevant factors such as family history, visual habits, current correction and any concerns you have noticed between examinations.
A single prescription provides useful information, but the pattern of change across several visits often gives a clearer picture of how the myopia is developing.
Measuring your child’s current prescription
Your child’s current refractive error is assessed to determine the optical correction needed for clear vision and to compare it with previous measurements where available.
Prescription change is an important part of monitoring myopia, but it is not the only measurement we consider. Two children with similar spectacle prescriptions may have different progression histories and eye-growth patterns.

Axial length measurement for every myopia assessment
At EMME Visioncare, axial length is measured for every child undergoing a myopia assessment.
Axial length refers to the distance from the front to the back of the eye. Childhood myopia is commonly associated with the eye becoming longer as it grows, so tracking axial length over time provides additional information about how the eye itself is changing.
Depending on the EMME branch, axial-length measurements are performed using optical biometry systems such as the Topcon MYAH or Essilor ARK SW9000.
Repeated measurements can help build a longitudinal record of eye growth. This can be useful when assessing progression and when monitoring a child who has already started a myopia-control treatment.
For a more detailed explanation of this measurement, read our guide: What Is Axial Length and Why Does It Matter in Childhood Myopia?
Why we do not rely on one number alone
There is no single axial-length value or prescription change that determines the right management plan for every child.
Measurements need to be interpreted in context. When assessing myopia progression, we consider factors including:
- your child’s age;
- current refractive error;
- previous prescription changes;
- axial-length measurements and trends;
- age when myopia first developed;
- eye-health findings;
- family history and other risk factors;
- current myopia-control treatment, if any; and
- practical factors that may affect treatment suitability.
Looking at these findings together helps provide a more meaningful assessment than treating any single measurement as a universal cut-off.
Establishing a baseline for future monitoring
For a child who has recently developed myopia, an assessment can provide useful baseline measurements that can be compared with future examinations.
For a child whose myopia is already progressing, previous and current measurements can help us understand the pattern of change and whether active myopia-control options should be discussed.
And for children who are already undergoing myopia control, follow-up measurements help assess how the eyes are changing over time rather than assuming that a treatment is working simply because vision remains clear.
What happens after the assessment?
Once the findings have been reviewed, your optometrist can explain what they mean in practical terms and discuss the next step with you.
Depending on your child’s measurements, progression history, eye health and individual circumstances, this may involve continued monitoring or a discussion about suitable myopia-control options.
There is no single treatment that is automatically best for every child. Options differ in how they are worn or used, their suitability requirements and the practical commitments involved.
In the next section, we compare the main myopia-control options available and explain the factors that may make one approach more suitable than another.
Compare Myopia Control Options
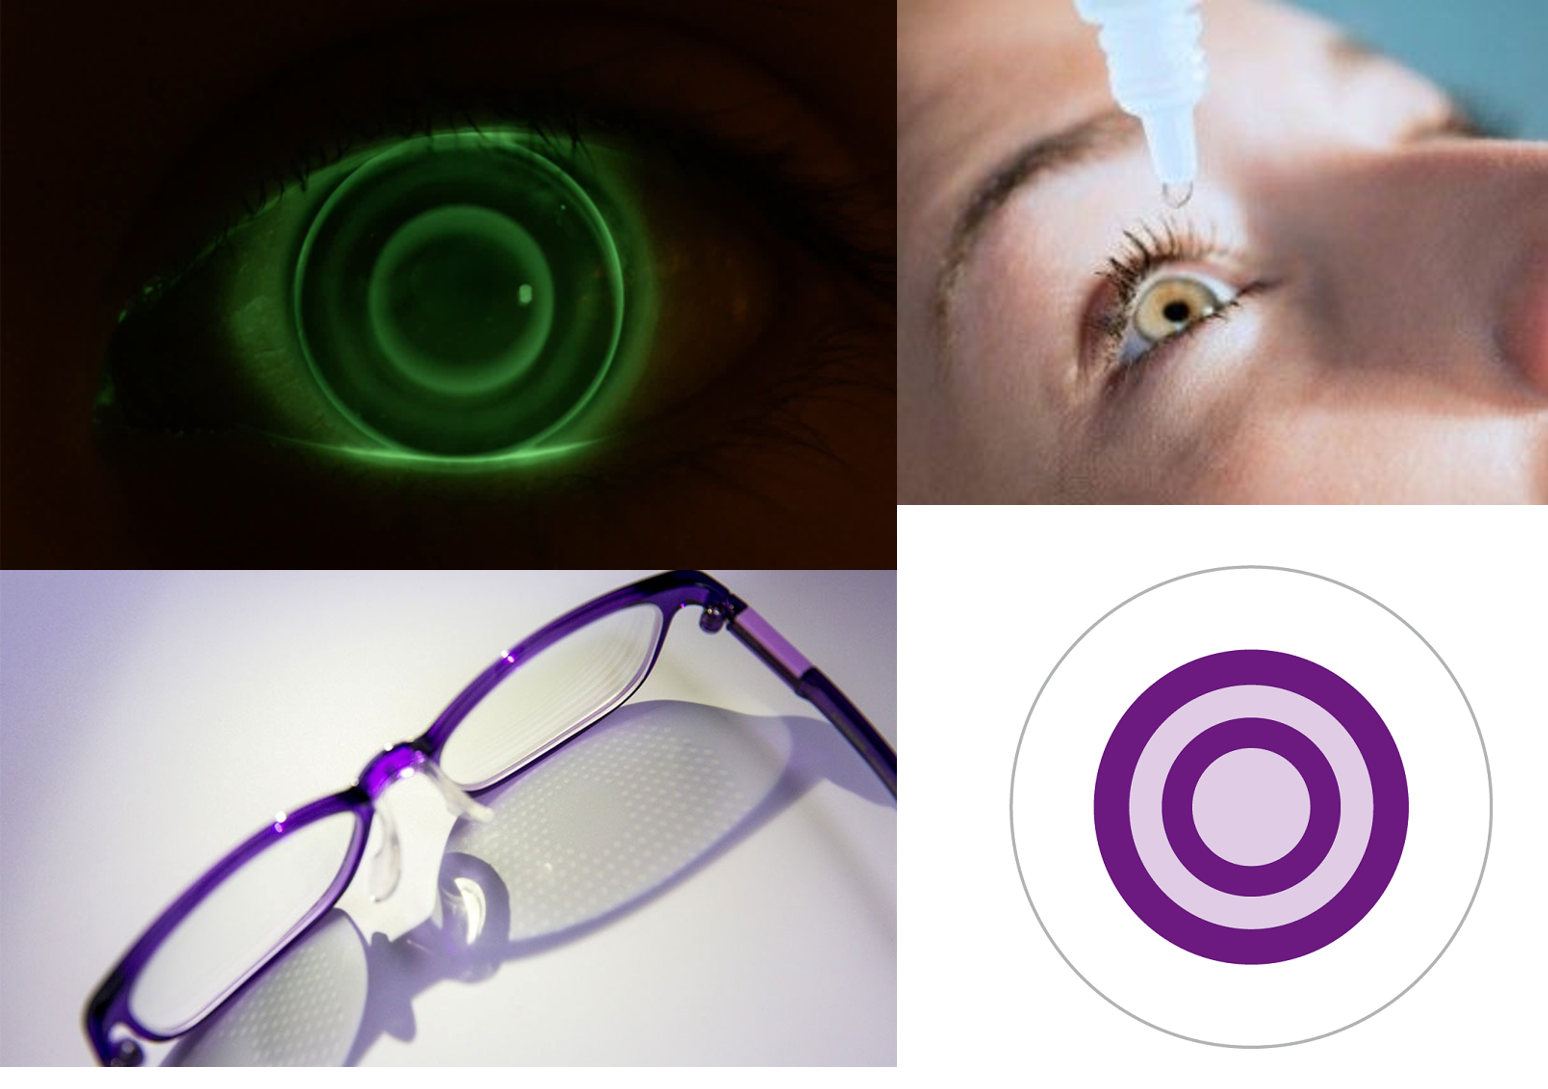
There are several evidence-based approaches available to help slow childhood myopia progression. These include specialised spectacle lenses, myopia-control contact lenses, overnight Ortho-K lenses and pharmacological treatments such as atropine.
There is no single myopia-control treatment that is best for every child. The most appropriate option depends on factors such as your child’s age, prescription, progression history, eye health, axial-length measurements, lifestyle and ability to manage the treatment safely.
At EMME Visioncare, we first assess how your child’s myopia is progressing before discussing the options that may be suitable.
Myopia-control options at a glance
| Option | How it is used | May suit children who | Important considerations |
|---|---|---|---|
| Ortho-K | Custom rigid contact lenses worn overnight | Prefer clear daytime vision without glasses or daytime contact lenses | Requires appropriate fitting, good lens hygiene, regular wear and follow-up |
| Myopia-control spectacle lenses | Specialised spectacles worn during the day | Prefer a non-contact-lens option that fits easily into everyday life | Consistent wear, appropriate frame fit and accurate lens positioning are important |
| MiSight 1 day | Daily disposable soft contact lenses worn during the day | Are suitable for contact lenses and prefer freedom from spectacles during the day | Requires contact-lens suitability, handling ability and appropriate wear habits |
| Atropine | Prescription eye drops used under medical supervision | May benefit from pharmacological treatment as part of their myopia-management plan | Requires prescribing and monitoring by an ophthalmologist; concentration and suitability are individual clinical decisions |
| Lifestyle measures | Healthy outdoor and near-work habits | All children can benefit from sensible visual habits | Support myopia management but should not be treated as a replacement for clinically indicated myopia-control treatment |
The most suitable option depends on the individual child. Assessment and ongoing monitoring help determine which approach is appropriate and whether changes are needed over time.
Ortho-K: overnight contact lenses
Orthokeratology, or Ortho-K, uses specially fitted rigid contact lenses that are worn during sleep. The lenses temporarily reshape the front surface of the cornea so that the child can usually see clearly during the day without wearing glasses or contact lenses.
Ortho-K can also be used as a myopia-control strategy in suitable children. The vision-correction effect and the myopia-control effect are related but distinct: the temporary corneal reshaping provides clearer daytime vision, while research has also shown that Ortho-K can help slow axial elongation in children with myopia.
Ortho-K may be particularly attractive for children who are active in sport or who prefer not to wear spectacles during the day.
However, it is not suitable for every child. Successful Ortho-K wear requires appropriate corneal assessment and lens fitting, consistent overnight wear, careful lens handling and hygiene, and regular follow-up.
Learn more about Ortho-K assessment and fitting at EMME
Myopia control glasses: MiYOSMART and Stellest 2.0
For children who prefer spectacles, specialised myopia-control lenses provide clear vision while incorporating optical designs intended to help slow myopia progression.
These differ from ordinary single-vision spectacle lenses. Standard single-vision glasses correct blurred vision, but they are not specifically designed to control myopia progression.
Myopia-control spectacles can be a practical option because they do not require contact-lens insertion, removal or cleaning. They may therefore suit younger children or families who prefer a spectacle-based approach.
The spectacles still need to be worn as recommended, and appropriate frame selection and lens positioning are important so that the lenses perform as intended.
Spectacle-lens options available for myopia management include:
- HOYA MiYOSMART myopia-control spectacle lenses; and
- Essilor Stellest 2.0 myopia-control spectacle lenses.
The choice of spectacle lens should still be based on the child’s prescription, measurements, frame fit, lifestyle and overall management plan rather than brand alone.
MiSight 1 day: daily disposable myopia-control contact lenses
MiSight 1 day is a daily disposable soft contact lens designed to provide clear vision while also helping to slow myopia progression in children.
Because each pair is discarded after use, there is no need to clean or store the lenses overnight. For suitable children, this can make daily disposable contact lenses a convenient way to combine vision correction and myopia control.
They may be particularly useful for children who prefer not to wear spectacles during school, sport or other daytime activities.
However, age alone does not determine whether a child is ready for contact lenses. The child needs to be able to insert and remove the lenses appropriately, follow hygiene instructions and wear them according to professional advice.
Eye health, prescription and contact-lens suitability also need to be assessed before fitting.
Learn more about MiSight 1 day for childhood myopia
Atropine eye drops
Atropine eye drops are another evidence-based approach used in childhood myopia management. Different atropine concentrations have been studied, and the appropriate concentration, potential benefits and possible side effects need to be considered for the individual child.
Atropine is a prescription medication and is not the same as an optical treatment such as spectacles, MiSight or Ortho-K.
Where pharmacological treatment may be appropriate, EMME can refer or co-manage with an ophthalmologist as required. The ophthalmologist can assess whether atropine is suitable, prescribe the medication and monitor the treatment medically.
Atropine may sometimes form part of a broader myopia-management plan rather than being considered in isolation.
Outdoor time and healthy visual habits
Lifestyle remains an important part of childhood myopia management. Regular outdoor time and sensible near-work habits are beneficial behaviours for children, particularly in a highly near-work-intensive environment such as Singapore.
Useful habits may include spending regular time outdoors, taking breaks from prolonged near work and avoiding unnecessarily close viewing distances when reading or using digital devices.
However, lifestyle changes should not be presented as a substitute for myopia-control treatment when a child is already showing clinically significant progression and active management is considered appropriate.
For a more detailed explanation, read our guide to screen time, outdoor time and childhood myopia .
Which myopia-control option is best for my child?
Rather than choosing a treatment based only on a brand name or a headline effectiveness percentage, the more useful question is:
“Which option is appropriate for my child’s eyes, progression pattern and everyday life?”
When discussing myopia-control options at EMME, we consider factors such as:
- your child’s age and age of myopia onset;
- current prescription and previous prescription changes;
- axial-length measurements and progression over time;
- eye-health and corneal findings;
- degree of myopia and astigmatism;
- contact-lens suitability where relevant;
- school, sport and other lifestyle requirements;
- the child’s ability to handle and care for contact lenses;
- family preferences and practical considerations; and
- response to any myopia-control treatment already being used.
Sometimes a spectacle-based option may be the most practical choice. Another child may be better suited to Ortho-K or daily disposable contact lenses. In other situations, ophthalmologist involvement or continued monitoring may be appropriate.
The aim is not to select the same treatment for every child, but to build a myopia-management plan around the individual child and monitor how their eyes respond over time.
How effective are myopia-control treatments?
Research supports several approaches for slowing childhood myopia progression, but treatment results should be interpreted carefully. Studies differ in the ages of children involved, treatment duration, baseline prescription, adherence, study design and whether progression is measured by prescription change, axial elongation or both.
For this reason, percentages reported for different treatments should not automatically be compared as though every treatment was tested under identical conditions.
If you would like a deeper review of the research, see: How Effective Are These Myopia Control Treatments?
Start with the assessment, not the product
If you are unsure whether Ortho-K, myopia-control spectacles, MiSight or another approach is appropriate, you do not need to choose before your appointment.
A myopia assessment allows us to review your child’s prescription, progression history, axial length, eye health and individual circumstances before discussing suitable options.
The next step is then ongoing monitoring: checking whether the chosen approach remains suitable and how your child’s eyes are changing over time.
Monitoring & Next Steps
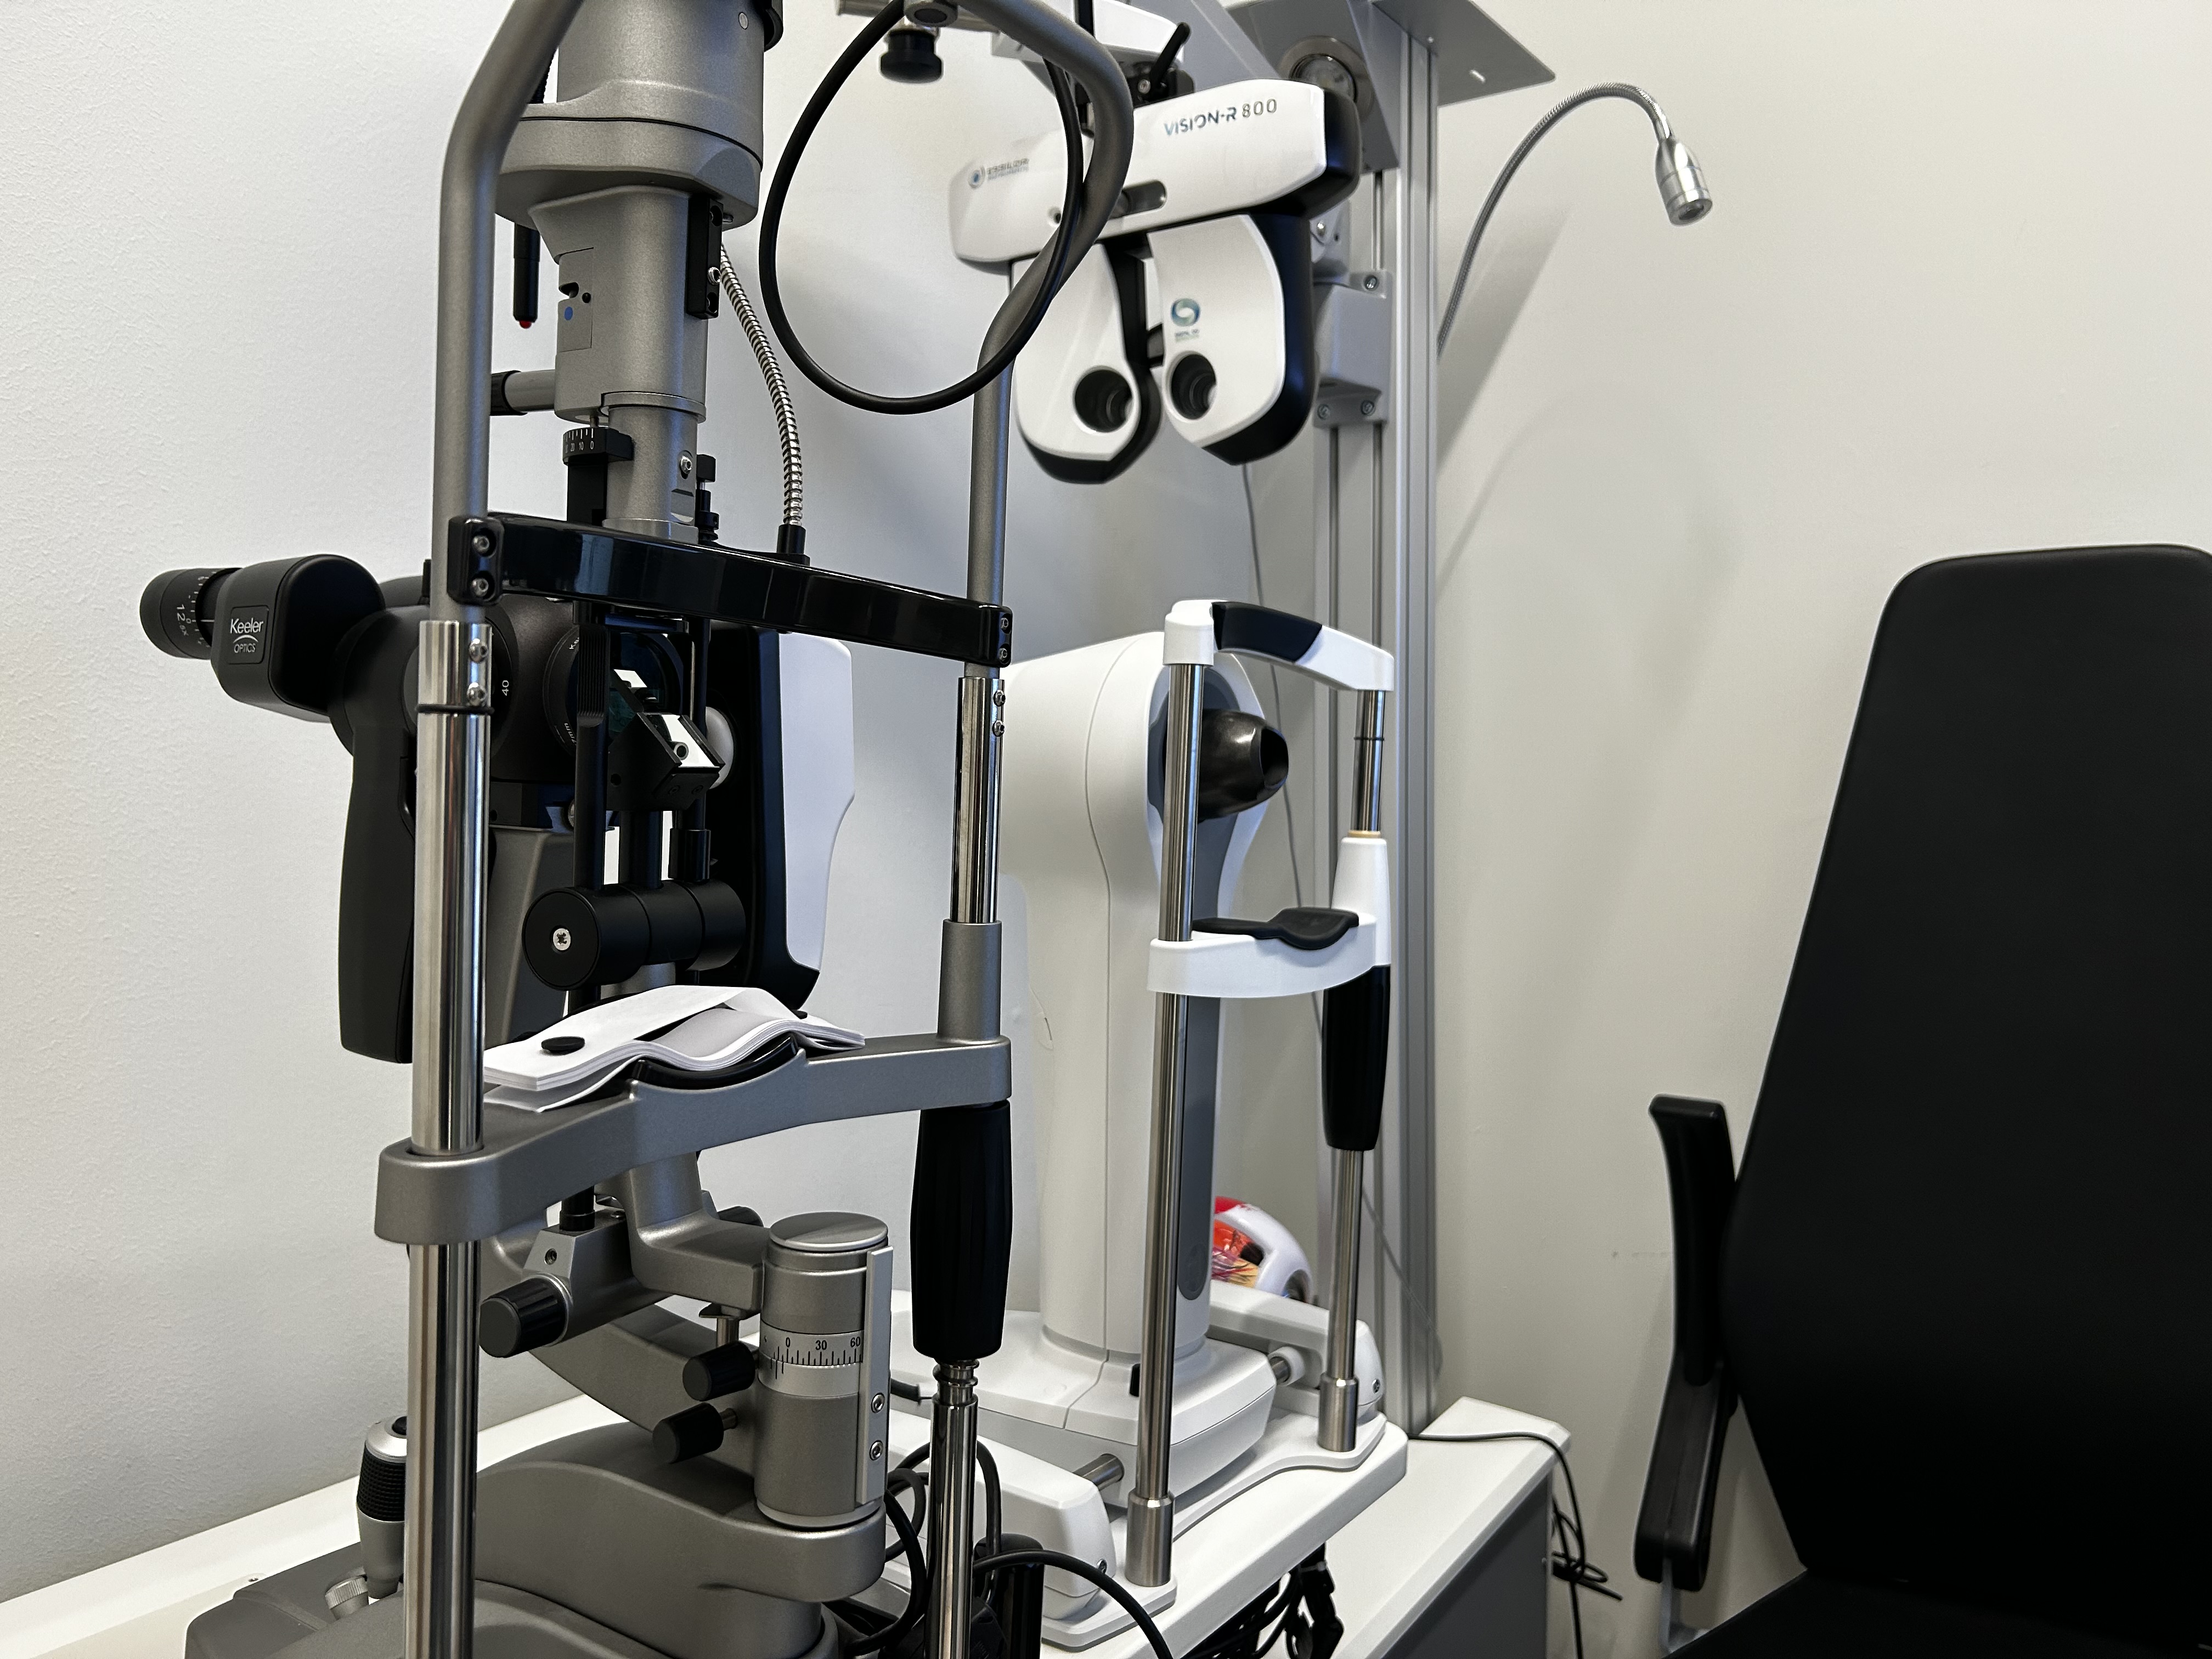
Myopia management does not end once a child starts wearing a particular spectacle lens, contact lens or other treatment.
Children continue to grow, and their eyes can continue to change. Regular follow-up helps us understand whether the chosen approach remains suitable and how the child’s myopia is progressing over time.
The goal is not to assume that a treatment is working simply because vision is clear, but to monitor the measurements that show how the eyes are changing.
How do we monitor myopia progression?
At follow-up visits, your optometrist may review several measurements and clinical findings, including:
- changes in your child’s spectacle or contact-lens prescription;
- axial-length measurements and trends over time;
- visual acuity and quality of vision;
- eye-health findings;
- how well the chosen treatment is being worn or used; and
- any practical concerns, discomfort or difficulties your child is experiencing.
Looking at these findings together gives a more useful picture than relying on a single measurement or one visit alone.
Why axial-length monitoring remains important
Axial length helps us monitor how the eye itself is growing. At EMME Visioncare, axial length is measured for every child undergoing a myopia assessment and can be compared with future measurements to help evaluate changes over time.
This is particularly useful because clear vision does not necessarily mean that myopia progression has stopped.
If you would like to understand this measurement in more detail, read: What Is Axial Length and Why Does It Matter in Childhood Myopia?
What if my child’s myopia continues to progress?
No myopia-control treatment can guarantee that progression will stop completely. Children respond differently, and some may continue to show prescription or axial-length changes despite treatment.
If progression continues, this does not automatically mean that a treatment has “failed”. Your optometrist can review the pattern of change together with treatment use, eye health, age and other clinical findings.
Depending on the situation, the next step may involve:
- continuing the current approach with further monitoring;
- reviewing how consistently the treatment is being used;
- reassessing whether another myopia-control option may be more suitable;
- considering whether a combination or alternative management approach should be discussed; or
- referral or co-management with an ophthalmologist where appropriate.
How often should my child be reviewed?
The appropriate follow-up schedule depends on the child, the treatment being used and the clinical findings.
A child who has recently started a new treatment may require different follow-up from a child who has been stable over several visits. Ortho-K and contact-lens wear also involve fitting, eye-health and lens-care considerations that need appropriate review.
Your optometrist will advise when the next examination or myopia review is appropriate based on your child’s individual management plan.
What happens at a myopia assessment at EMME?
A myopia assessment is designed to help parents understand how their child’s eyes are changing and what the available next steps may be.
- Review your child’s history — including previous prescriptions, age of myopia onset and relevant family or lifestyle factors.
- Assess current vision and prescription — to determine the correction required and compare with previous findings where available.
- Measure axial length — to help evaluate and monitor eye growth.
- Assess the overall clinical picture — including age, progression history, eye health and other relevant findings.
- Discuss suitable options — where active myopia control may be appropriate.
- Plan ongoing monitoring — so future measurements can be compared over time.
The purpose of the assessment is not to automatically place every child on the same treatment. It is to provide enough information to make an informed decision about monitoring and myopia management.
Why choose EMME for a myopia assessment?
EMME Visioncare provides myopia assessment and management within a primary eye-care and optometry setting in Singapore.
Our approach includes:
- axial-length measurement for every child undergoing a myopia assessment;
- assessment of prescription change together with eye-growth trends;
- access to multiple myopia-control options rather than a single-treatment approach;
- specialised contact-lens and Ortho-K assessment where suitable;
- ongoing follow-up and monitoring; and
- referral or co-management with ophthalmologists when indicated.
Myopia assessments are available through EMME Visioncare at The Cathay and Jelita Mall.
When should you consider booking a myopia assessment?
A myopia assessment may be useful if:
- your child has recently been diagnosed with myopia;
- their prescription has been increasing between eye examinations;
- myopia developed at a younger age and you are concerned about future progression;
- your child is already using myopia control and you would like their progression reviewed; or
- you would like professional guidance before choosing between myopia-control options.
If you are concerned about how quickly your child’s myopia is changing, you can also read our guide: When Should Parents Worry About Myopia Progression?
How much does a myopia assessment cost?
A myopia assessment at EMME Visioncare costs S$50, inclusive of GST. Any written report is charged separately at S$50.
Myopia control and Ortho-K at Jelita Mall
At our Jelita Mall branch (#02-17, 293 Holland Road), Ortho-K and children's myopia control are looked after by founder and optometrist Shawn Au, who has more than 25 years of experience in primary eye care. Open daily 10am–8pm. Book via WhatsApp 9383 8569.
Book a Myopia Assessment
If your child’s prescription is changing or you would like to understand whether myopia control may be appropriate, the first step is an assessment rather than choosing a treatment on your own.
We can review your child’s prescription, axial length, progression history and eye health, then explain the management options that may be suitable.